Showing posts with label HAI. Show all posts

Persistent Pathogens

 image

Credit CDC PHIL


# 6757


While exotic emerging viruses tend to garner the greatest headlines, old school bacterial nemeses like C. diff, S. aureus, and A. baumannii exact an impressive toll each year, killing tens of thousands of hospitalized patients and adding billions of dollars in health care costs.


This oft quoted assessment from the CDC on the burden of Hospital Acquired Infections in the United States is from 2010.


A new report from CDC updates previous estimates of healthcare-associated infections. In American hospitals alone, healthcare-associated infections account for an estimated 1.7 million infections and 99,000 associated deaths each year. Of these infections:

  • 32 percent of all healthcare-associated infection are urinary tract infections
  • 22 percent are surgical site infections
  • 15 percent are pneumonia (lung infections)
  • 14 percent are bloodstream infections


Hospitals are engaged in a perpetual warfare against the spread of infection - and while progress is being made - many pathogens continue to slip past the infection control safeguards.


The American Journal of Infection Control - the official publication of APIC – provides a sobering overview of this daily battle, and while infection control techniques are improving, bacteria can be masters at evading even the most stringent measures.


One of the toughest bacteria that hospitals must deal with is multidrug-resistant (MDR) Acinetobacter baumannii, which in recent years has made headlines as the cause of difficult to treat wound infections among our troops serving in the Middle East.


Acinetobacter (of which there are many varieties, but A. baumannii is most often linked to human infection ) are ubiquitous in nature, and can be found in  soil, water, animals and humans. A very hardy species, they can survive for extended period of time on inanimate surfaces, making them difficult to control in a health care setting.


Yesterday the AJIC carried an article on just how tough eradicating this bacteria really is.


The effect of terminal cleaning on environmental contamination rates of multidrug-resistant Acinetobacter baumannii

Paula Strassle, BS, Kerri A. Thom, MD, J. Kristie Johnsonm, PhD(ABMM), Surbhi Leekha, MBBS, MPH, Matthew Lissauer, MD, FACS, Jingkun Zhu, MS, Anthony D. Harris, MD, MPH

We evaluated the prevalence of multidrug-resistant Acinetobacter baumannii environmental contamination before and after discharge cleaning in rooms of infected/colonized patients. 46.9% of rooms and 15.3% of sites were found contaminated precleaning, and 25% of rooms and 5.5% of sites were found contaminated postcleaning. Cleaning significantly decreased environmental contamination of A baumannii; however, persistent contamination represents a significant risk factor for transmission. Further studies on this and more effective cleaning methods are needed.


The full text to this study are available on the AJIC website, but we’ve also a brief summary via a press release.


Hospital cleaning protocol ineffective against A. baumannii

Washington, November 30, 2012 -- Current hospital cleaning protocol may be inadequate to rid patient rooms of multidrug-resistant (MDR) Acinetobacter baumannii, according to a study in the December issue of the American Journal of Infection Control, the official publication of the Association for Professionals in Infection Control and Epidemiology (APIC).


A team of researchers from the University of Maryland collected 487 cultures from 32 hospital rooms occupied by just-discharged patients with a known history of MDR A. baumannii both before and after terminal cleaning of the rooms. Over half of the rooms positive for the A. baumannii bacteria prior to cleaning remained contaminated after terminal cleaning had occurred.


Fifteen rooms (46.9 percent) and 41 sites (n=268, 15.3 percent) tested positive for MDR A. baumannii before cleaning. Post-cleaning, eight rooms (25 percent) and 12 sites (n=219, 5.5 percent) still tested positive for the pathogen. Sites with post-cleaning contamination included the floor (12.5 percent), call button (10 percent), door handle (9.4 percent) bedside table (7.4 percent), and supply cart (3.8 percent).


"Persistent room contamination serves as a potential reservoir for transmission and colonization of future room occupants," state the authors in the article. "Current cleaning techniques in terms of products used or thoroughness of cleaning may not be adequate in the decontamination of this pathogen."


Acinetobacter baumannii is a type of bacteria that has become increasingly prevalent in healthcare facilities and is resistant to most antibiotics. Infections from this pathogen primarily occur in very ill, wounded, or immunocompromised patients. The germ can remain on wet or dry surfaces for longer than most other organisms, making it harder to eradicate.


"This study shows how difficult it is to ensure removal of particularly resistant organisms from the environment even upon thorough discharge cleaning," said Anthony D. Harris, MD, MPH, lead study author and professor of epidemiology and public health at the University of Maryland School of Medicine. "With new, innovative means of monitoring cleaning processes that we have incorporated since the study was done, coupled with other infection control efforts, we are seeing lower rates of A. baumannii at our hospital."


The good news is that while difficult, control of these organisms is possible with the right measures. We’ve looked at the problem of controlling HAIs frequently in the past.  A few examples include:


That said, the subjects of HAIs and resistant bacteria are most consistently (and frankly, better) addressed by Maryn McKenna on her excellent Superbug Blog, and was a major focus of her book SUPERBUG: The Fatal Menace Of MRSA.

Both of which are highly recommended.

»» Read More

Revisiting An Earlier Fungal Meningitis Outbreak


image

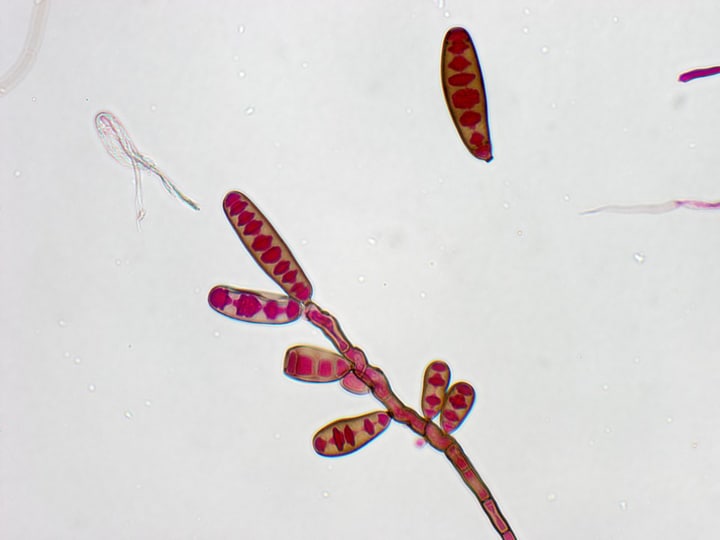
Exserohilum rostratum – Credit CDC


# 6646


One of the basic tenets of modern medicine is Primum non nocere, or `First, do no harm’.  And while that is undoubtedly the goal of every practitioner, sadly, it doesn’t always work out that way.


Whether by accident, misdeed, or miscalculation - sometimes a patient’s health is made worse by the treatment they receive from the healthcare system.


When that happens it is called an Iatrogenic (from the Greek iatros, physician & genein, to produce) illness or injury.


HCAIs (Health Care Associated Infections) or HAIs (Hospital Acquired Infections) fall under the Iatrogenic umbrella, and according to the AHRQ :


HAIs are the most common complication of hospital care and are one of the top 10 leading causes of death in the United States, accounting for an estimated 1.7 million infections and 99,000 associated deaths in 2002. The financial burden attributable to these infections is estimated at $28 to $33 billion in excess health care costs each year.


As we watch the rising number of fungal meningitis cases among recipients of steroid preparations from an New England compounding pharmacy, it may surprise many to learn that a strikingly similar tragedy occurred a decade ago.


The year was 2002, and the origin was – once again – a compounding pharmacy, this time in South Carolina.  While number of cases was fewer - and the type of fungus was different - the narrative is hauntingly familiar. 


This from the CDC’s MMWR of December 2002:


Exophiala Infection from Contaminated Injectable Steroids Prepared by a Compounding Pharmacy --- United States, July--November 2002

In the United States, pharmacists compound medications to meet unique patient drug requirements or to prepare drug products that are not available commercially (1). In September 2002, the North Carolina Division of Public Health (NCDPH) was notified of two cases of meningitis caused by a rare fungus in patients who had received epidural injections at outpatient pain management clinics.


This report describes five cases of fungal infection associated with contaminated drugs prepared at a compounding pharmacy. Clinicians should consider the possibility of improperly compounded medications as a source of infection in patients after epidural or intra-articular injections.


In this case, the contamination was eventually linked to an improperly maintained and operated autoclave.


An investigation of compounding pharmacy A by the South Carolina Board of Pharmacy (SCBP) found improper performance of an autoclave with no written procedures for autoclave operation, no testing for sterility or appropriate checking of quality indicators, and inadequate clean-room practices as outlined in the American Society of Health-System Pharmacists (ASHP) guidance for pharmacy-prepared sterile products (2)


Of particular concern was the revelation that: Cases occurred up to 152 days following an injection.


The source of suspected contamination at the NECC facility in Massachusetts has not been determined, but yesterday the FDA announced that unopened vials from one of the batches of recalled methylprednisolone acetate were found to harbor Exserohilum rostratum.


Last night, the Annals of Internal Medicine published a perspective by John R. Perfect, M.D. who dealt with the South Carolina outbreak ten years ago. Dr. Perfect is Chief of the Division of Infectious Diseases at Duke University Medical Center. 


The article is free, informative, and much worth reading in its entirety.


Iatrogenic Fungal Meningitis: Tragedy Repeated

John R. Perfect, MD

Ann Intern Med. 18 October 2012

Recent reports of fungal meningitis cases caused by contaminated corticosteroid injections demand that we remember prior lessons learned, while scrambling to care for currently affected persons even before all the facts are in hand.


In 2002, the Centers for Disease Control and Prevention (CDC) detailed 5 cases of Exophiala (Wangiella) dermatitidis meningitis or arthritis related to contaminated, injectable, preservative-free methylprednisolone acetate prepared from a compounding pharmacy (1).

(Continue . . .)

»» Read More

The Flight Of The Bacterial Intruder

image

Credit CDC PHIL


# 6625


HCAIs (Health care associated Infections) or HAIs (Hospital acquired infections) constitute a major threat to life, health, and the cost of medical care in this country, and around the world. This oft quoted assessment from the CDC on the burden of Hospital Acquired Infections in the United States is from 2010.


A new report from CDC updates previous estimates of healthcare-associated infections. In American hospitals alone, healthcare-associated infections account for an estimated 1.7 million infections and 99,000 associated deaths each year. Of these infections:

  • 32 percent of all healthcare-associated infection are urinary tract infections
  • 22 percent are surgical site infections
  • 15 percent are pneumonia (lung infections)
  • 14 percent are bloodstream infections


A 2009 report The Direct Medical Costs of Healthcare-associated Infections in U.S. Hospitals and the Benefits of Prevention finds:


Applying two different Consumer Price Index
(CPI) adjustments to account for the rate of inflation in hospital resource prices, the overall annual direct medical costs of HAI to U.S. hospitals ranges from $28.4 to $33.8 billion (after adjusting to 2007 dollars using the CPI for all urban consumers) and $35.7 billion to $45 billion (after adjusting to 2007 dollars using the CPI for inpatient hospital services).


As you can imagine, hospitals are engaged in a perpetual battle against the spread of infection - and while progress is being made - many pathogens continue to slip past the infection control safeguards.


A study from the University of Leeds recently published in the Journal Building and Environment may provide a clue as to why the infection control measures being used today have failed to curb the spread of bacteria in the hospital setting.


Bioaerosol Deposition in Single and Two-Bed Hospital Rooms: A Numerical and Experimental Study

M.F. King, C.J. Noakes, P.A. Sleigh, M.A. Camargo-Valero


You’ll find the abstract, along with figures and tables from this article, at the link above. But the full paper is behind a pay wall. The University of Leeds website, however, has a synopsis of this research project, which is excerpted below:.


Superbugs ride air currents around hospital wards

Published Thursday 11th October 12

Hospital superbugs can float on air currents and contaminate surfaces far from infected patients’ beds, according to University of Leeds researchers.


The results of the study, which was funded by the Engineering and Physical Sciences Research Council (EPSRC), may explain why, despite strict cleaning regimes and hygiene controls, some hospitals still struggle to prevent bacteria moving from patient to patient.


It is already recognised that hospital superbugs, such as MRSA and C-difficile, can be spread through contact. Patients, visitors or even hospital staff can inadvertently touch surfaces contaminated with bacteria and then pass the infection on to others, resulting in a great stress in hospitals on keeping hands and surfaces clean.


But the University of Leeds research showed that coughing, sneezing or simply shaking the bedclothes can send superbugs into flight, allowing them to contaminate recently-cleaned surfaces.


PhD student Marco-Felipe King used a biological aerosol chamber, one of a handful in the world, to replicate conditions in one- and two-bedded hospital rooms. He released tiny aerosol droplets containing Staphyloccus aureus, a bacteria related to MRSA, from a heated mannequin simulating the heat emitted by a human body. He placed open Petri dishes where other patients’ beds, bedside tables, chairs and washbasins might be and then checked where the bacteria landed and grew.


The results confirmed that contamination can spread to surfaces across a ward. “The level of contamination immediately around the patient’s bed was high but you would expect that. Hospitals keep beds clean and disinfect the tables and surfaces next to beds,” said Dr Cath Noakes, from the University’s School of Civil Engineering, who supervised the work. “However, we also captured significant quantities of bacteria right across the room, up to 3.5 metres away and especially along the route of the airflows in the room.”


“We now need to find out whether this airborne dispersion is an important route of spreading infection,” added co-supervisor Dr Andy Sleigh.

(Continue . . .)


While we often think first of viruses when it comes to airborne transmission of illness, some types of bacteria (e.g. Legionella, Mycoplasma pneumonia, Tuberculosis) are easily aerosolized and transmitted.


This study is not the first to identify the airborne spread of Staphylococcus aureus, but they have developed an ingenious way to quantify it.


Regarding MRSA and C. Difficile the Journal of The Royal Society published a review in 2009 called:


Airborne transmission of disease in hospitals

I. Eames, J. W. Tang,Y. Li and P. Wilson

(EXCERPT)

MRSA can survive on surfaces or skin scales for up to 80 days and spores of Clostridium difficile may last even longer. MRSA can be transmitted in aerosol from the respiratory tract but commonly attaches to skin scales of various sizes. The distance of travel depends on the size of the scale, the larger falling to the floor within 1–2 m, the smaller travelling the entire length of the ward.

<SNIP>

Clostridium difficile spores are thought to spread in the air and can be found near a patient carrying the organism (Roberts et al. 2008). However, unlike MRSA, they are rarely isolated from air samples.


Not surprisingly, in 2010, we saw a study published in the AJIC: American Journal of Infection Control that found that the more roommates you have during a hospital stay, the greater chance you will have of contracting an HAI like MRSA or C. Diff.


Exposure to hospital roommates as a risk factor for health care–associated infection

Meghan Hamel, MSc, Dick Zoutman, MD, FRCPC, Chris O'Callaghan, DVM, MSc, PhD


The authors used this study to promote the idea  of making private (or at least, semi-private) rooms the norm in Canadian hospitals. While acknowledging that it would involve considerable up-front costs, they believe the long-term savings would be considerable.


All of this highlights the great challenges involved in substantially reducing the incidence of HAIs in our health care facilities.


Solutions must not only include stringent hand hygiene and improved cleaning methods, but engineering solutions as well.


For more on the prevention of Hospital Acquired Infections you may wish to visit the CDC’s HAI PAGE.


image


Or revisit some of these earlier blogs on hospital acquired infections.


HPA: Healthcare-Associated Infection (HCAI) Survey
A Barrier To Good Hand Hygiene
Study: Hospital Uniforms And Bacteria
Study: HAIs, Universal Surveillance, & MRSA


And finally, the subject of HAIs is often addressed by Maryn McKenna on her excellent Superbug Blog, and was a major focus of her book SUPERBUG: The Fatal Menace Of MRSA.


Both are highly recommended.

»» Read More

HPA: Healthcare-Associated Infection (HCAI) Survey


# 6340


The UK’s HPA has released a comprehensive survey of antimicrobial use, and HCAI (Healthcare-Associated Infections), across 114 hospitals (99 NHS acute trusts and 5 independent sector organizations), providing us with a snapshot of conditions between September and November 2011.


Although the full global burden of HCAIs or HAIs (Hospital Acquired Infections) is unknown and underappreciated, even in countries with modern healthcare facilities they constitute a major threat to life and health.


The following is an oft quoted assessment from the CDC on HAI’s (Hospital Acquired Infections) in the United States back in 2010.

A new report from CDC updates previous estimates of healthcare-associated infections. In American hospitals alone, healthcare-associated infections account for an estimated 1.7 million infections and 99,000 associated deaths each year. Of these infections:

  • 32 percent of all healthcare-associated infection are urinary tract infections
  • 22 percent are surgical site infections
  • 15 percent are pneumonia (lung infections)
  • 14 percent are bloodstream infections


The subject of HAIs is often addressed by Maryn McKenna on her excellent Superbug Blog, and was a major focus of her book SUPERBUG: The Fatal Menace Of MRSA. Both are highly recommended.


The HPA is working to reduce the incidence of HAIs in the UK, and according to their latest report, progress has been made. The greatest reductions have been made in MRSA bloodstream infections and C. difficile infections.


Of special note, Enterobacteriaceae (includes E. coli, Klebsiella spp.,Enterobacter spp. and others) were the most frequently reported organisms associated with HCAI, infecting roughly .9% of the patient population, and making up nearly 1/3rd of all infections.


Links to the 140 page preliminary report, 144 page appendices, and a 16  page FAQ at the link below.


English National Point Prevalence Survey on Healthcare-associated Infections and Antimicrobial Use, 2011: preliminary data

English PPS on HCAI and AMU 2011

Authors:

HPA

Publication date: May 2012

Synopsis

The Health Protection Agency (HPA) coordinated the fourth National Point Prevalence Survey (PPS) on healthcare-associated infection (HCAI) and first National PPS on antimicrobial use (AMU) in England. This survey is not directly comparable to previous surveys.


The aims of the PPS were to determine the burden of HCAI and AMU in acute hospitals and to use the results to identify priority areas for the future.

Key points

  • The prevalence of healthcare-associated infections (HCAI) was 6.4% in 2011 compared to 8.2% in 2006.
  • The most frequent HCAIs detected were respiratory tract, urinary tract and surgical site infections.
  • The prevalence of antimicrobial use (AMU) was 34.7%. This is the first time AMU was measured nationally. This provides a baseline for future monitoring.
  • The prevalence of HCAIs, AMU and device use was highest in intensive care units, which relates in part to the complexity and vulnerability of patients in this setting.

Download full publication

English National Point Prevalence Survey on Healthcare-Associated Infections and Antimicrobial Use, 2011 - Appendices (PDF, 3.3 MB)


PPS Frequently Asked Questions (PDF, 654 KB)


English National Point Prevalence Survey on Healthcare-associated Infections and Antimicrobial Use, 2011 (PDF, 1.9 MB)


While there is much to be gleaned from these reports, a few highlights from the FAQ include:


3.1 What is the overall prevalence of HCAI in English hospitals?

The overall prevalence of HCAI in acute hospitals was 6.4%.The prevalence in NHS acute trusts was 6.5% Independent sector organisation had a lower prevalence of HCAI of 2.2%.

It is not appropriate to compare the prevalence between these hospital types because they represent distinct case mixes, patient populations and specialties. Further the numbers included were very small in paediatric and independent hospitals and these results should be interpreted with caution.


3.2 Does a prevalence of 6.4% mean that if I go in to hospital I have a one in sixteen chance of getting a HCAI?

No. This means that at any time one in sixteen inpatients in hospital will have a HCAI. A prevalence survey counts the number of patients with HCAI at any point in time.

People with HCAI tend to stay in hospital longer and those patients who stay in hospital for longer periods of treatment tend to be more seriously ill and therefore more at risk of contracting HCAI. The large majority of patients are successfully treated in hospital and go home without acquiring a HCAI.


3.3 Can you tell me what my chance is of contracting HCAI during my hospital stay?


No. This is not shown by the current prevalence survey. In order to calculate how likely a person is to get a HCAI an incidence study would be required. This would look at all patients who were treated within the hospital on a regular basis over a defined time period.


The other focus of this survey was to determine the level of AMU (Antimicrobial Usage) in acute care hospitals in England.  The report found:


The overall prevalence of AMU was 34.7%. The prevalence of AMU was greatest in the independent sector hospitals (46.7%) compared with NHS organisations at 34.3%. The prevalence of AMU in adults was 35.3% and in paediatrics 28.7%. AMU prevalence was greatest in ICU at 60.8%.


The total number of antimicrobials prescribed in the survey was 25,942 for 18,219 (34.7%) patients, which equates to 1.4 AM per patient prescribed antimicrobials. AMU were most frequently prescribed for community acquired infections (53.0%). Thirteen percent of patients were on an antimicrobial (AM) for surgical prophylaxis; 30.3% of surgical prophylaxis was administered for greater than one day.


The majority of AMU was for respiratory tract infections (30.9%). The second most common reason for AMU was skin, soft tissue, bone and joint infections (19.0%).


The use of a standardized survey technique should go a long ways towards developing better year-to-year comparisons of HCAIs and AMU in UK facilities, and will facilitate comparisons with other EU countries that have adopted similar surveys.

»» Read More

Global Clean Your Hands Day: 2012


Five steps to 5 May 2012 - What's YOUR plan?


# 6316


Tomorrow, May 5th, is being promoted by the World Health Organization as global  CLEAN YOUR HANDS DAY - to encourage HCWs (Healthcare workers) to improve and sustain hand hygiene practices around the world.


While exact numbers are unknown, it is estimated that tens . . . perhaps hundreds of millions of people around the world are adversely affected by what are largely preventable  health care-associated infections (HCAI) each year.


Most of these infections could be prevented by HCWs maintaining good hand hygiene – cleaning their hands properly, and at the appropriate time.


Last year we saw the introduction of the 5 moments for hand hygiene campaign.


image

image


This from the World Health Organization.


WHO Save lives: clean your hands global annual campaign

Date: 5 May 2012

Each year, hundreds of millions of patients all around the world are affected by health care-associated infections (HCAI). Although HCAI is the most frequent adverse event in health care, its true global burden has been unknown because of the difficulty in gathering reliable data. However, recent work by WHO and others highlights that developing countries are more affected. Most health care-associated infections are preventable through good hand hygiene – health-care workers cleaning hands, at the right times and in the right way.

The Save Lives: clean your hands global annual campaign, launched in 2009, is a day in which WHO is committed to 'bringing people together to improve and sustain hand hygiene'. Overall it is an opportunity to:

  • be part of a global movement to improve hand hygiene and receive acknowledgement of this from WHO;
  • be one of the leaders helping to prevent HCAI in your country; subsequently saving lives;
  • receive support for moving from commitment to action at the point of patient care;
  • share your knowledge and successes with others;
  • join a network of countries that have already committed to sustained hand hygiene campaigning; and
  • demonstrate your commitment to making patient safety a priority.
Related links


Lest anyone think that this is just a problem in developing countries, the CDC reports that every year about 2 million Americans get a hospital associated infection (HAI), and as many as 100,000 people die each year as a result.


A point driven home repeatedly by Maryn McKenna in her book, Superbug: The Fatal Menace of MRSA which I reviewed here.


Remarkably, Maryn points out that 50% of health care workers fail to consistently wash their hands between patients.


Whether you work in a healthcare setting or not, today would be a good day to visit the CDC’s hand hygiene website, where you will find many resources, including a link to a new iPad/iPhone application called iScrub.


image


To round out this entry, some oldies but goodies from the AFD archives.


Doing The Hand Jive
Referral: Maryn McKenna On Hand Hygiene
Gonna Wash Those Germs Right Off Of My Hands


A collection of Hand Washing posters can be found at:


http://www.cdc.gov/handhygiene/Resources.html


And lastly, a return engagement by that consummate entertainer, one that Maryn McKenna  introduced me to a few years ago . . .  the one you all know and  love . . give it up for GERMY, in the award winning all singing, all dancing production of Soapacabana!

»» Read More

A Barrier To Good Hand Hygiene


# 5939


It sounds counter-intuitive. 


That the use of latex (or vinyl) gloves could contribute to reduced hand hygiene compliance in health care settings. 


But that is exactly what a study - published in the December issue of Infection Control and Hospital Epidemiology – has uncovered.


The study, which was conducted at 15 hospitals in the UK, found that hand hygiene compliance – even in this age of heightened awareness of infection control - was `disappointingly low’.


Overall hand hygiene compliance was observed to be just 47.7%, while the use of gloves was associated with a further decrease to just 41%.


It would appear that the use of gloves can lead to a false sense of security, and the result is a reduction in hand hygiene.


The following press release comes from SHEA, the  Society for Healthcare Epidemiology of America. 


Latex gloves lead to lax hand hygiene in hospitals, study finds

CHICAGO -- Healthcare workers who wear gloves while treating patients are much less likely to clean their hands before and after patient contact, according to a study published in the December issue of Infection Control and Hospital Epidemiology, the journal of the Society for Healthcare Epidemiology of America. This failure of basic hand hygiene could be contributing to the spread of infection in healthcare settings, the researchers say.


Glove use is appropriate for situations when contact with body fluids is anticipated or when patients are to be managed with contact precautions. However, use of gloves should not be considered a substitute for effective hand hygiene practices taking place before and after patient contact. Although gloves can reduce the number of germs transmitted to the hands, germs can sometimes still get through latex. Hands can also be contaminated by "back spray" when gloves are removed after contact with body fluids.


The researchers, led by Dr. Sheldon Stone of the Royal Free Hospital NHS Trust, observed more than 7,000 patient contacts in 56 intensive care and acute care of the elderly wards in 15 United Kingdom hospitals, making this one of the largest and most detailed studies on gloves and their impact on hand hygiene. Overall, the study found that hand hygiene compliance was "disappointingly low," at just 47.7 percent. Compliance was even lower in instances where gloves were worn, dipping to just over 41 percent.


"The chances of hands being cleaned before or after patient contact appear to be substantially lower if gloves were being worn," said Dr. Stone, the principal investigator. "We call this the phenomenon of the 'Dirty Hand in the Latex Glove.'"

(Continue . . . )


Cite: Christopher Fuller, Joanne Savage, Sarah Besser, Andrew Hayward, Barry Cookson, Ben Cooper, Sheldon Stone. The Dirty Hand in the Latex Glove: A Study of Hand-Hygiene Compliance When Gloves Are Worn. Infection Control and Hospital Epidemiology 32:12 (December 2011)


Given the huge burden of HAIs (Hospital Acquired Infections), the subject of hand hygiene comes up frequently in this blog. 


You’ll find a lot more on this subject in last month’s Giving Germs A Helping Hand, which looked at low handwashing compliance among doctors and other healthcare providers.


On May 5th of this year the World Health Organization promoted a CLEAN YOUR HANDS DAY  to encourage HCWs to improve and sustain hand hygiene practices around the world.


Clean Care is Safer Care
First Global Patient Safety Challenge
Clean Care is Safer Care


Additionally, the CDC’s hand hygiene website  has many resources, including a link to a new iPad/iPhone application called iScrub.


image


To round out this entry, some oldies but goodies from the AFD archives.

Doing The Hand Jive
Hand Hygiene Among Doctors Exposed
Gonna Wash Those Germs Right Off Of My Hands
»» Read More

Giving Germs A Helping Hand


# 5892


One hundred and sixty-three years ago, a Hungarian physician named Ignaz Semmelweis published a controversial medical book called Etiology, Concept and Prophylaxis of Childbed Fever.


At the time, childbed - or puerperal fever - was a common cause of mortality and morbidity among postpartum women. Semmelweis demonstrated that it could be greatly reduced by simply having doctors wash their hands before performing gynecological exams.


Sure, that makes sense today, but at the time his theories were considered radical (Pasteur wouldn’t come up with his `germ theory’ for another 17 years).


Besides, it was outrageous to suggest that doctors might actually be causing disease and death among their patients.


Semmelweis was ridiculed, ostracized and eventually forced to leave his hospital post. He died at the age of 47 in an asylum, a broken man.


More than 160 years later, infection control professionals continue to drum the message of proper hand hygiene into HCWs (Health Care Workers), yet lapses remain common.


A discouraging report from the Irish Independent.


Doctors 'worst' at basic hand hygiene

By Eilish O'Regan Health Correspondent

Wednesday October 12 2011

Nearly one in four doctors fails to clean their hands between patients -- increasing the risk of passing on potentially life-threatening infection, a damning report revealed yesterday.


The survey of hand hygiene in 36 acute hospitals revealed that doctors were the worst offenders (61pc) and that, overall, nearly three in 10 staff were not following the basic rule of infection control.

(Continue . . .)


The actual audit report is available on the HPSC (Health Protection Surveillance Center) website.


June 2011: Hand Hygiene Audit Results (Period 1)

File Size: (278kB)
Publication Date: 11 October 2011

Frequently Asked Questions on Hand Hygiene Audit Results

File Size: (167kB)
Publication Date: 11 October 2011


The `good news’ is that nurses – who likely have the greatest direct contact with patients – were the best at hand hygiene, with a compliance rate of just over 80%.


image


The `bad news’ is that this survey may not accurately reflect the level of compliance when auditors are not present.   The report explains:


3.  Limitations of Auditing Hand Hygiene with Direct Observation 

The results may not be reflective of healthcare worker compliance at all times. Compliance with hand hygiene is measured by auditors observing healthcare workers undertaking patient care. It is well recognised that workers will change their behaviour, if aware that they are being observed (Hawthorne effect).


However, it is also known that this effect wears off over time and that healthcare workers under observation may not be aware (due to the many competing demands on their attention) of the presence of the auditor. In addition, the purpose of auditing is to improve practice, therefore any action that improves compliance increases patient safety. Auditors are requested to give immediate feedback to ward staff following an audit, thereby increasing awareness and knowledge of hand hygiene. 


While overall compliance was just under 75%, the goal is to raise that to 90% by 2013.


Given the heavy burden of HAIs (Hospital Acquired Infections), on May 5th of this year the World Health Organization promoted a CLEAN YOUR HANDS DAY  to encourage HCWs to improve and sustain hand hygiene practices around the world.


Clean Care is Safer Care
First Global Patient Safety Challenge
Clean Care is Safer Care

The goal of Clean Care is Safer Care is to ensure that infection control is acknowledged universally as a solid and essential basis towards patient safety and supports the reduction of health care-associated infections and their consequences.


As a global campaign to improve hand hygiene among health-care workers, SAVE LIVES: Clean Your Hands is a major component of Clean Care is Safer Care. It advocates the need to improve and sustain hand hygiene practices of health-care workers at the right times and in the right way to help reduce the spread of potentially life-threatening infections in health-care facilities.

Below you’ll find some resources from the WHO, including posters, PDF files, and articles.

image

image

Five Moments for Hand Hygiene

The newly developed Five Moments for Hand Hygiene has emerged from the WHO Guidelines on Hand Hygiene in Health Care (Advanced Draft) to add value to any hand hygiene improvement strategy. Quite simply, it defines the key moments for hand hygiene, overcoming misleading language and complicated descriptions. It presents a unified vision and promotes a strong sense of ownership.


Not only does the Five Moments align with the evidence base concerning the spread of HAI but it is interwoven with the natural workflow of care and is designed to be easy to learn, logical and applicable in a wide range of settings. Find out more about your Five Moments by clicking the links below.


Whether you work in a healthcare setting or not, today would be a good day to visit the CDC’s hand hygiene website, where you will find many resources, including a link to a new iPad/iPhone application called iScrub.

image


To round out this entry, some oldies but goodies from the AFD archives.


Doing The Hand Jive
Hand Hygiene Among Doctors Exposed
Gonna Wash Those Germs Right Off Of My Hands


And finally a collection of Hand Washing posters can be found at:


Suitable For Framing

»» Read More

Study: Hospital Uniforms And Bacteria


image

Photo Credit CDC PHIL 


# 5798


HAIs, or Hospital Acquired Infections, take an incredible toll on patient’s health and our health care system every year. 


According to the HHS, they rank among the top ten leading causes of death in the United States, and accounted for an estimated 1.7 million infections and 99,000 associated deaths in 2002.


While hospitals are constantly working to reduce the incidence of HAIs, it is a daunting task.  We live in a  germy world, and the opportunities to spread bacteria in a healthcare setting are abundant.


Studies have shown that while compliance rates are improving, up to 50% of health care workers in the United States may fail to consistently wash their hands between patients (cite).


This year, the World Health Organization designated May 5th as global  CLEAN YOUR HANDS DAY - to encourage HCWs (Healthcare workers) to improve and sustain hand hygiene practices around the world (see A Movement With Five Moments).


One of the ongoing concerns regarding nosocomial transmission of pathogens has been that lab coats, neckties, and long sleeves might help to spread harmful bacteria from patient to patient in a healthcare facility.


In response, in 2007 the NHS banned the wearing of long-sleeved white coats, wristwatches, and neckties by HCWs in hospital wards, and in 2009 the AMA (American Medical Assoc.) considered a “bare below the elbows” dress code during their annual meeting, but decided the issue needed more study (see Lab Coat Legislation).


The rap against lab coats and neckties has primarily been that they are not usually freshly laundered every day.


One recent study showed that 62% of doctors surveyed waited 2-weeks or longer to launder their coats. 


While that sounds like a bit of a red flag, earlier this year we saw a study (see The Long And The Short Of It) that found no statistical difference between the amount of bacteria of freshly laundered short sleeve uniforms versus infrequently laundered white coats after only 8 hours wear.


And what isn’t known is how well pathogens transfer from contaminated uniforms to the surrounding environment, or on to patients.


Today, another study appears in APIC’s American Journal of Infection Control, that looks at the prevalence of harmful bacteria on uniforms worn in a university-affiliated hospital in Israel.


The areas of each uniform tested were the abdominal zone, sleeves' ends and pockets.


Potentially pathogenic bacteria were isolated from the uniforms of 85 participants (63%) and were detected in half the samples taken.


They found 21 cultures from the nurses uniforms and 6 from physician uniforms grew multi-drug resistant pathogens, including 8 that grew MRSA.


While a bit disconcerting, given the environment in which these uniforms are worn, and previous studies we’ve seen, these results are not all that surprising.


The abstract can be read at:


AJIC: American Journal of Infection Control
Volume 39, Issue 7 , Pages 555-559, September 2011

Nursing and physician attire as possible source of nosocomial infections

Conclusion

Up to 60% of hospital staff’s uniforms are colonized with potentially pathogenic bacteria, including drug-resistant organisms. It remains to be determined whether these bacteria can be transferred to patients and cause clinically relevant infection.


In an Elsevier Health Services Press Release (Doctors' and nurses' hospital uniforms contain dangerous bacteria majority of the time, study shows), APIC President Russell Olmsted, MPH, CIC is quoted as saying:


"It is important to put these study results into perspective. Any clothing that is worn by humans will become contaminated with microorganisms. The cornerstone of infection prevention remains the use of hand hygiene to prevent the movement of microbes from these surfaces to patients.


New evidence such as this study by Dr. Wiener-Well is helpful to improve the understanding of potential sources of contamination but, as is true for many studies, it raises additional questions that need to be investigated."


Last year, according to Infection Control Today, the American Medical Association (AMA)  announced plans to begin formal research on "textile transmission of infections" singling out the "physician's white lab coat as a primary concern associated with textile transmission of infections."


Promising new technologies, including bacteria-resistant fabrics, are being developed in hopes that they will reduce HAIs.


But for now, more research is needed to determine just how much of a role contaminated uniforms really play in the spread of harmful pathogens to patients in the hospital.

»» Read More

Fomite to Fingers To Face: A Triple Play Combination


 image

 Photo Credit – CDC 

# 5741


Fomites are any surface or object that can become contaminated with viral or bacterial pathogens and that can act as a vehicle of transmission. 


Surfaces like the touch screen on your bank’s ATM, the door knob to a public restroom, or the the handle of a shopping cart are touched by scores of people every day.  


And some of those people, undoubtedly, are leaving behind bacteria and viruses you really don’t want to get.


Last June (see Firefighters & MRSA Revisited) I wrote of a study by researchers from the University of Washington that looked for – and found – MRSA (Methicillin-resistant Staphylococcus aureus) contaminated surfaces at fire houses in Snohomish county.


MRSA was detected in 4% of samples taken from places such as kitchens, bathrooms, and rescue vehicles – and researchers also found 30% of firefighters who volunteered to be tested were colonized with either MRSA or S. aureus in their noses.


While fomites have long been suspected of playing a significant role in the transmission of diseases, it has only been in recent years that we’ve learned how remarkably resilient many of these pathogens are once they are deposited on an inanimate surface.


The 2007 study Significance of Fomites in the Spread of Respiratory and Enteric Viral Disease by Stephanie A. Boone,& Charles P. Gerba found that most viruses survived longer on nonporous surfaces (metal or plastic), and that respiratory viruses (RSV, HPIV, influenza virus, coronavirus, and rhinovirus) could remain viable for hours or even days.


Under the right conditions, enteric viruses - like Rotavirus, Norovirus, and Hepatitis A - have been known to survive on fomites from weeks to months


It’s a germy world out there, and most people touch their face 10 to 20 times each hour, providing ample opportunities for pathogens to move from fomite to fingers to face.


All of which serves as prelude to a study that appears in the August issue of the American Journal of Infection Control that surveyed the hand hygiene knowledge and beliefs of 71 nurses, infection preventionists and hospital environmental services managers.


Individual differences in judgments of hand hygiene risk by health care workers

Anne Collins McLaughlin, PhD Fran Walsh, PhD


Participants were asked to assess their perceived risk of contracting or spreading an infection in 16 real-life situations. 


The authors found that across all levels, healthcare workers perceived surfaces as safer to touch than a patient’s skin, despite studies that have implicated fomites in the chain of disease transmission. 


The authors comment:

"Despite the dangers that fomites present, this knowledge may not be common enough among HCWs for them to understand the level of risk when touching surfaces and then touching patients."


Studies have shown that although compliance rates are improving, 50% of health care workers in the United States fail to consistently wash their hands between patients (cite).


Hospital acquired infections (HAIs) remain a huge problem, and exact a terrible toll on patients and their families.


This from the HHS.


HHS Action Plan to Prevent Healthcare-Associated Infections: Introduction

Healthcare-associated infections exact a significant toll on human life. They are among the top ten leading causes of death in the United States, accounting for an estimated 1.7 million infections and 99,000 associated deaths in 2002.


Of course, this isn’t just a problem in the United States, but also around the world. 


So this year the World Health Organization designated May 5th as global  CLEAN YOUR HANDS DAY - to encourage HCWs (Healthcare workers) to improve and sustain hand hygiene practices around the world (see A Movement With Five Moments).


image


For some earlier blogs on the importance of fomites in the transmission of disease, and the value of hand hygiene you may wish to revisit:


CMAJ: Infectious Risks In Family Doctor’s Offices
Hand Hygiene Among Doctors Exposed
MDs Behaving Badly
Suitable For Framing


And lastly . . . to start your week off with a smile, a return engagement by that consummate entertainer, one that Maryn McKenna  introduced me to a couple of years ago . . .  the one you all know and  love . . give it up for GERMY, in the award winning all singing, all dancing production of Soapacabana!

Stick around for the outtakes!

»» Read More

Lab Coat Legislation


image


# 5544


In recent years lab coats, long sleeves, neckties, and jewelry in the healthcare setting have all come under increased scrutiny as concerns over HAIs (Hospital Acquired Infections) – including MRSA – have escalated.


Long sleeves, many fear, could facilitate the transfer of bacteria from one patient to the next. 


In 2007, Britain’s NHS decided to ban the wearing of long-sleeved white coats, wristwatches, and neckties by healthcare providers in hospital wards.


In the United States, the AMA (American Medical Assoc.) considered a “bare below the elbows” dress code during their annual meeting in 2009, but decided the issue needed more study. 


Some healthcare facilities – like the Mayo Clinic – have pushed ahead with their own dress codes to address the issue.  


Today UPI is reporting that New York State legislators are considering mandating a `hygienic dress code for medical professionals’ – one that may eventually prohibit the wearing of jewelry, wristwatches, neckties, long sleeves, and the iconic white lab coat.


N.Y. may ban germy doctor ties, lab coats

Published: May 8, 2011 at 2:04 AM


The article goes on to say that if passed, a 25-person advisory council – to be appointed by the commissioner of health – would provide recommendations for a new medical dress code.


While `textile transfer’ of bacteria in the healthcare setting makes sense, the scientific evidence linking sleeve cuffs and neckties to actual HAIs is scant, mostly anecdotal, and sometimes even contradictory.


While not exactly a smoking gun, in 2009 researchers at the Virginia Commonwealth University Medical Center in Richmond demonstrated that large inoculums of MRSA,vancomycin-resistant enterococci (VRE), and pan–resistant Acinetobacter (PRA) bacteria could be transferred from a white cotton lab coat to pigskin.


The rap against lab coats and neckties has primarily been that they are not usually freshly laundered every day.


One study showed that 62% of doctors surveyed waited 2-weeks or longer to launder their coats. 


But earlier this year, a study (see The Long And The Short Of It) found no statistical difference between the amount of bacteria of freshly laundered short sleeve uniforms versus infrequently laundered white coats after only 8 hours wear.


The argument can still be made, however, that long sleeve cuffs (and neckties) are more likely to come in contact with a series of patients than the fabric of short sleeved shirts.


With an estimated 99 thousand deaths each year in the United States from nosocomial (hospital acquired) infections each year, the stakes are enormous. 


Yet the science proving the supposed benefits of a dress code change is sparse. 


So, for now at least, the the debate over the fate of lab coats, long sleeves, and neckties in the United States continues with no resolution in sight.

»» Read More

A Movement With Five Moments


# 5540


Studies have shown that although compliance rates are improving, 50% of health care workers in the United States fail to consistently wash their hands between patients (cite).


Compliance rates in many developing countries are even lower, and these lapses in good hand hygiene no doubt lead to hundreds of thousands of HAIs (Hospital Acquired Infections) every year (see HAI: Hospital Acquired Infections).


So today, May 5th, is promoted by the World Health Organization as global  CLEAN YOUR HANDS DAY - to encourage HCWs (Healthcare workers) to improve and sustain hand hygiene practices around the world.


Clean Care is Safer Care

First Global Patient Safety Challenge
Clean Care is Safer Care

The goal of Clean Care is Safer Care is to ensure that infection control is acknowledged universally as a solid and essential basis towards patient safety and supports the reduction of health care-associated infections and their consequences.


As a global campaign to improve hand hygiene among health-care workers, SAVE LIVES: Clean Your Hands is a major component of Clean Care is Safer Care. It advocates the need to improve and sustain hand hygiene practices of health-care workers at the right times and in the right way to help reduce the spread of potentially life-threatening infections in health-care facilities.


Below you’ll find some resources from the WHO, including posters, PDF files, and articles on today’s activities.


image

image


Five Moments for Hand Hygiene


The newly developed Five Moments for Hand Hygiene has emerged from the WHO Guidelines on Hand Hygiene in Health Care (Advanced Draft) to add value to any hand hygiene improvement strategy. Quite simply, it defines the key moments for hand hygiene, overcoming misleading language and complicated descriptions. It presents a unified vision and promotes a strong sense of ownership.


Not only does the Five Moments align with the evidence base concerning the spread of HAI but it is interwoven with the natural workflow of care and is designed to be easy to learn, logical and applicable in a wide range of settings. Find out more about your Five Moments by clicking the links below.

Tools for 5 Moments - English


Semmelweis Revisited

(excerpted from an earlier blog)


One hundred and sixty-four years ago, a Hungarian physician named Ignaz Semmelweis published a controversial medical book called Etiology, Concept and Prophylaxis of Childbed Fever.


Childbed, or puerperal fever, was a major cause of mortality and morbidity among postpartum women, and Semmelweis demonstrated in his Viennese hospital that its incidence could be greatly reduced by having doctors wash their hands before performing gynecological exams.


His theories were considered radical (Pasteur wouldn’t come up with his `germ theory’ for another 17 years), and went against all currently accepted medical science.  Diseases, as everyone knew, were caused by imbalances in one of the `four humours’ in the body, to be cured by bloodletting, and had nothing at all to do with washing one’s hands.


Besides, it was outrageous to suggest that doctors might actually be causing disease and death among their patients.


Semmelweis was ridiculed, ostracized and eventually forced to leave his hospital post.  He moved to Pest, and frustrated by the lack of acceptance of his theories, often denounced the medical community.


His fortunes and reputation suffered greatly due to his unrelenting advocacy of hand hygiene.


Eventually, he was committed to an asylum, a broken man, where he died at the age of 47.  It was only in the years after his death, with the addition of Pasteur’s findings, that his theories became universally accepted.


Incredibly, and despite 150 years of evidence of proven efficacy, doctors and health care professionals around the world are still not as diligent with hand washing as they should be.


And those lapses cost thousands of lives, and billions of dollars in additional medical expenses, every year.


This from the CDC on HAI’s (Hospital Acquired Infections)

CDC strives to understand how healthcare-associated infections happen and to develop appropriate interventions. A new report from CDC updates previous estimates of healthcare-associated infections. In American hospitals alone, healthcare-associated infections account for an estimated 1.7 million infections and 99,000 associated deaths each year. Of these infections:

  • 32 percent of all healthcare-associated infection are urinary tract infections
  • 22 percent are surgical site infections
  • 15 percent are pneumonia (lung infections)
  • 14 percent are bloodstream infections


And this is just  the United States, globally the numbers are much, much higher.

Sadly, many of these complications could have been prevented by more stringent hand hygiene.


»» Read More